Home / Conditions / Pulmonary hypertension: diagnosis and treatment in Bangalore
Condition · Pulmonary hypertensionPulmonary hypertension: diagnosis and treatment in Bangalore
Raised pressure in the lung arteries has five quite different causes, and almost everything about treatment depends on which one a patient has. Dr. Manjunath M Negigoudara assesses and treats pulmonary hypertension at KIMS Hospital, Electronic City, Bengaluru, and has published Indian data on pulmonary hypertension in fibrotic lung disease in the European Respiratory Journal.
250+
Lung transplants personally managed
780+
Thoracic transplants at KIMS
India’s 1st
Redo double lung transplant
ERJ · JHLT
Peer-reviewed publications
What is pulmonary hypertension?
The right side of the heart pumps blood through the lungs at a pressure far lower than the left side uses for the rest of the body. When that pressure rises, the right ventricle has to work against resistance it was never built for. It copes for a while by thickening, then it begins to dilate, and eventually it fails. Most of what we call the symptoms of pulmonary hypertension are really the symptoms of a right ventricle under strain.
The 2022 ESC/ERS guidelines define pulmonary hypertension as a mean pulmonary artery pressure above 20 mmHg measured directly at catheterisation. The threshold was lowered from 25 mmHg in 2022, which brought a group of patients with milder elevation into the diagnosis, and those patients need identifying because their outcomes are worse than people with normal pressures.
The delay is the problem
Pulmonary hypertension is characteristically diagnosed late, because its first symptom is exertional breathlessness and that gets attributed to asthma, weight, anaemia or being out of shape. Unexplained breathlessness that has been investigated without an answer, particularly with blackouts on exertion, deserves an echocardiogram specifically looking at the right heart.

Dr. Manjunath M Negigoudara
Transplant Pulmonologist, KIMS
Next available
What are the five groups of pulmonary hypertension?
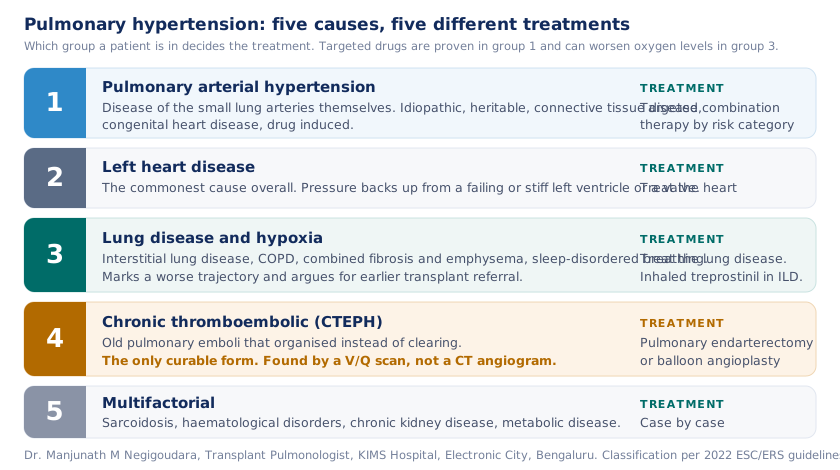
This is the part patients are rarely told clearly, and it is the most consequential thing on this page. Pulmonary hypertension is classified into five groups by cause. The expensive targeted drugs are proven in group 1. In some of the other groups they do not help, and in group 3 they can actively make oxygen levels worse.
| Group | Cause | What treatment looks like |
|---|---|---|
| 1 Pulmonary arterial hypertension | Disease of the small lung arteries themselves. Idiopathic, heritable, connective tissue disease, congenital heart disease, drug induced. | Targeted combination therapy, escalated by risk category. The group where modern drugs have transformed survival. |
| 2 Left heart disease | The commonest cause overall. Pressure backs up from a failing or stiff left ventricle or a diseased valve. | Treat the heart. Targeted pulmonary arterial hypertension drugs are not indicated and may cause harm. |
| 3 Lung disease and hypoxia | Interstitial lung disease, COPD, combined fibrosis and emphysema, sleep-disordered breathing, high altitude. | Treat the lung disease, correct hypoxia. Inhaled treprostinil has evidence specifically in interstitial lung disease. Marks a worse trajectory and argues for earlier transplant referral. |
| 4 Chronic thromboembolic | Old pulmonary emboli that organised instead of clearing. | Potentially curable. Pulmonary endarterectomy surgery or balloon pulmonary angioplasty, with lifelong anticoagulation. |
| 5 Multifactorial | Sarcoidosis, haematological disorders, chronic kidney disease, metabolic disease. | Directed at the underlying condition. Managed case by case. |
Which type of pulmonary hypertension is curable?
Group 4, chronic thromboembolic pulmonary hypertension, is the only potentially curable form, and it is regularly missed. The reason is that the test which finds it is not the test most people get. A CT pulmonary angiogram can look unremarkable in chronic thromboembolic disease. A ventilation-perfusion scan is far more sensitive for it, and the ESC/ERS guidelines state that every patient with unexplained pulmonary hypertension should have one.
Many patients with this condition never had a diagnosed clot. The original event was silent, or was treated as a chest infection. If you have been told you have pulmonary hypertension and have not had a V/Q scan, that is worth asking about directly, because the difference between a curable and a lifelong illness turns on it.
How is pulmonary hypertension diagnosed?
Echocardiogram as the screening test
An echocardiogram estimates pulmonary pressure from the speed of a regurgitant jet across the tricuspid valve. It is indirect, it can be technically difficult, and it both over-calls and under-calls the diagnosis. Its real value is in assessing right ventricular size and function, and in looking for left-sided heart disease that would place the patient in group 2. A raised estimated pressure on echocardiography is a reason to investigate, not a diagnosis.
Right heart catheterisation as the standard
This is the only test that measures pressure directly. It provides mean pulmonary artery pressure, pulmonary artery wedge pressure and pulmonary vascular resistance, and that combination is what separates group 1 from group 2 and establishes severity. No patient should be committed to long-term targeted therapy on the basis of an echocardiogram alone.
Finding the cause
Alongside catheterisation, the workup includes a V/Q scan to exclude chronic thromboembolic disease, high-resolution CT of the chest for lung disease, full pulmonary function testing with DLCO, an autoimmune panel, an overnight sleep study where sleep-disordered breathing is suspected, a six-minute walk test, and blood natriuretic peptide levels for risk assessment and monitoring.
Pulmonary hypertension in fibrotic lung disease
This is the group Dr. Manjunath has published on. His 2023 paper in the European Respiratory Journal, Pulmonary hypertension in patients with Progressive Fibrosing Interstitial Lung Disease (PF-ILD) referred for Lung Transplantation, a retrospective study from India, examined exactly this population in an Indian transplant referral setting. Details are on the publications page.
The clinical message is consistent. When pulmonary hypertension appears in someone with fibrotic lung disease, it marks a change in trajectory. Breathlessness becomes disproportionate to the extent of scarring on the scan, oxygen requirements climb, walk distance falls, and the prognosis worsens. Its presence is one of the clearest arguments for bringing forward a transplant assessment rather than continuing to observe.
It also means the treatment approach differs from group 1. The one exception with trial evidence is inhaled treprostinil, which improved exercise capacity in the INCREASE trial in pulmonary hypertension associated with interstitial lung disease. Otherwise the instinct to reach for pulmonary arterial hypertension drugs has to be resisted, because in diseased lung they can increase blood flow to areas that are not ventilating and drop oxygen saturation further. Related reading: interstitial lung disease and pulmonary fibrosis and IPF.
How is pulmonary hypertension treated?
For group 1 pulmonary arterial hypertension, treatment is risk-based and usually begins with combination therapy rather than a single drug, escalating to a prostacyclin agent when a patient remains at high risk. Patients are re-assessed at intervals using walk distance, natriuretic peptide levels, echocardiographic right ventricular function and functional class, and therapy is stepped up when they are not in a low-risk category.
Alongside drug treatment: supervised exercise training improves capacity, supplemental oxygen is used where saturation falls, anticoagulation is decided case by case except in chronic thromboembolic disease where it is lifelong, pregnancy carries very high risk and needs explicit counselling, and vaccination against influenza and pneumococcus matters more than in the general population.
When does pulmonary hypertension need a lung transplant?
For pulmonary arterial hypertension, referral is indicated when a patient stays in a high-risk category despite appropriate combination therapy including a prostacyclin agent, or when right heart failure is progressing, per the ISHLT 2021 consensus. Pulmonary arterial hypertension patients can deteriorate quickly, so referral is made while the patient is still able to complete an assessment.
For pulmonary hypertension complicating lung disease, the presence of pulmonary hypertension is itself the trigger to bring forward assessment. Where right heart failure is severe and a patient is deteriorating while waiting, ECMO can be used as a bridge. Read about lung transplantation and what it costs in Bangalore.
Consulting at KIMS Electronic City
Bring your echocardiogram report, any catheterisation report, HRCT images, pulmonary function tests with DLCO, V/Q scan if done, recent blood work and a full medication list. KIMS Hospital, Survey No. 37 and 38, PES University EC Campus, Hosur Road, Konappana Agrahara, Bengaluru 560100. Monday to Saturday, 9 AM to 5 PM, with evening and video consultations by prior appointment. Call or WhatsApp +91 79937 41199.
For patients from Bangalore, across India, and abroad
Bengaluru and Electronic City
The hospital is on Hosur Road opposite the PES University EC Campus, about 15 minutes from Silk Board via the elevated expressway. Patients attend from HSR Layout, Koramangala, Sarjapur Road, BTM Layout, Jayanagar, JP Nagar, Bannerghatta Road, Whitefield and Marathahalli, and from Bommasandra, Anekal, Chandapura and Attibele.
Karnataka and the rest of India
Referrals come from Mysuru, Mangaluru, Hubballi-Dharwad, Belagavi, Kalaburagi, Shivamogga, Tumakuru, Davangere and Ballari, and from Chennai, Coimbatore, Madurai, Salem, Hyderabad, Warangal, Vijayawada, Visakhapatnam, Tirupati, Kochi, Thiruvananthapuram, Kozhikode, Goa, Mumbai, Pune, Nagpur, Ahmedabad, Delhi NCR, Kolkata, Bhubaneswar, Guwahati, Lucknow, Patna, Ranchi and Raipur. Because pulmonary hypertension workup involves several tests, send your existing reports on WhatsApp first so the visit can be planned and duplicate testing avoided. Kempegowda International Airport is about 45 km away.
International patients
Patients are seen from Bangladesh, Nepal, Sri Lanka, the Maldives and Bhutan, from Oman, the UAE, Saudi Arabia, Iraq, Yemen, Kuwait, Bahrain and Qatar, from Kenya, Tanzania, Ethiopia, Uganda, Rwanda, Sudan, Nigeria and Ghana, and from Myanmar, Indonesia and Malaysia. The pathway is remote review over WhatsApp, a written opinion that can support a medical visa application, a three to four day evaluation visit including catheterisation where indicated, and video follow-up from home.
Related reading
- Interstitial lung disease, the commonest lung cause of group 3 pulmonary hypertension
- Pulmonary fibrosis and IPF
- Publications, including the 2023 European Respiratory Journal paper on this topic
- Advanced lung failure service
- Who needs a lung transplant
- Second opinion on a pulmonary hypertension diagnosis
- All lung conditions treated at KIMS Electronic City
References
The clinical statements on this page are drawn from the peer-reviewed literature and international guidelines listed below. Each link opens the source on PubMed.
- 2022 ESC/ERS Guidelines for the diagnosis and treatment of pulmonary hypertension.
- Inhaled Treprostinil in Pulmonary Hypertension Due to Interstitial Lung Disease.
- Ventilation-perfusion scintigraphy is more sensitive than multidetector CTPA in detecting chronic thromboembolic pulmonary disease as a treatable cause of pulmonary hypertension.
- Consensus document for the selection of lung transplant candidates: An update from the International Society for Heart and Lung Transplantation.
Frequently asked questions
Which doctor treats pulmonary hypertension in Bangalore?
What are the symptoms of pulmonary hypertension?
Can pulmonary hypertension be cured?
Is an echocardiogram enough to diagnose pulmonary hypertension?
What is the difference between pulmonary hypertension and pulmonary arterial hypertension?
Does pulmonary hypertension in lung fibrosis get treated with the same drugs?
When does pulmonary hypertension need a lung transplant?
Can I have my case reviewed remotely before travelling?
Next available
Book a consultation with Dr. Manjunath M Negigoudara
In person at KIMS Hospital, Electronic City, or by video