Home / Procedures / Rigid bronchoscopy: opening a blocked airway
Procedure · Therapeutic airwayRigid bronchoscopy: opening a blocked airway
When a central airway is blocked, collapsing or bleeding, a flexible scope is not enough. A rigid bronchoscope gives control of the airway and room to work, and it can relieve severe breathlessness within minutes. Performed by Dr. Manjunath M Negigoudara at KIMS Hospital, Electronic City, Bengaluru.
250+
Lung transplants personally managed
780+
Thoracic transplants at KIMS
India’s 1st
Redo double lung transplant
ERJ · JHLT
Peer-reviewed publications
Written for patients, not for journals
If you have searched for rigid bronchoscopy you will have found mostly research papers. That is a reasonable reflection of how specialised the procedure is, but it is not much help if you or a relative has been told you need one. This page explains what it is, why it is recommended, what the day involves and what the risks are, in ordinary language.

Dr. Manjunath M Negigoudara
Transplant Pulmonologist, KIMS
Next available
What is a rigid bronchoscopy?
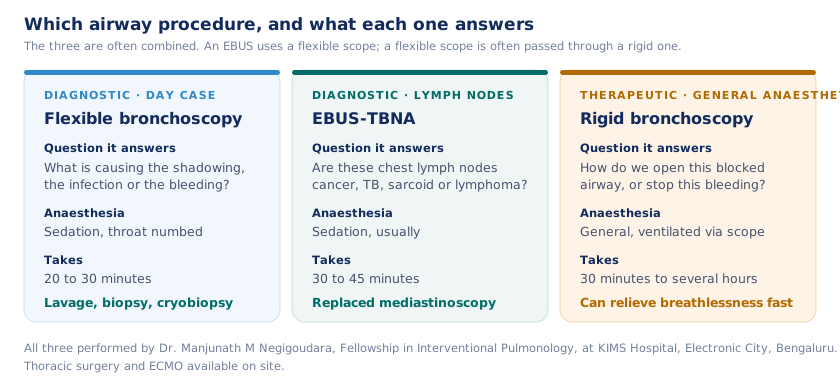
A straight, hollow metal tube, open at both ends, passed through the mouth and past the vocal cords into the windpipe under general anaesthesia. Unlike a flexible scope, it does not bend and cannot reach far into the smaller branches. What it offers instead is control.
Because the tube is open, the anaesthetist ventilates the patient through it, so breathing is maintained while the operator works. Because it is wide, several large instruments can pass at once, and suction is powerful enough to clear blood or thick secretions that would overwhelm a flexible scope. Because it is rigid, it can be used to core through obstructing tissue and to hold an airway open mechanically. In a crisis, the rigid scope is the instrument that secures the airway.
The simplest way to think about it
A flexible bronchoscope is for finding out what is wrong. A rigid bronchoscope is for doing something about it when the problem is in a large central airway and the situation will not wait.
When is rigid bronchoscopy needed?
A blocked central airway
A tumour growing into the windpipe or a main bronchus, whether from the lung itself or spread from elsewhere, progressively narrows the airway. Breathlessness worsens, a wheeze or noisy breathing appears, and eventually the lung beyond the blockage collapses or becomes infected. Clearing the obstruction restores airflow. The AQuIRE registry, the largest prospective series of therapeutic bronchoscopy for malignant central airway obstruction, found the procedure technically successful in the large majority of cases with measurable improvement in breathlessness and quality of life. In a patient whose cancer is being treated with chemotherapy, radiotherapy or immunotherapy, this is often what makes those treatments possible by keeping the patient well enough to receive them.
Narrowing from scarring
Not all obstruction is cancer. Airways narrow after prolonged ventilation or tracheostomy, after tuberculosis, from inflammatory conditions, and after lung transplantation. Scar narrowing is frequently curable, treated with dilatation and with cutting or cryotherapy to release the scar, sometimes with a temporary stent while healing takes place.
Coughing up blood
Heavy bleeding from the airway is life-threatening not because of blood loss but because blood floods the airways and prevents breathing. A rigid scope allows the good lung to be protected, the bleeding side to be isolated, and the bleeding point to be treated. This is one of the clearest indications and one where a flexible scope alone is inadequate.
A foreign body
Something inhaled and lodged in an airway, common in children and in adults who have choked while eating or during dental work. Small soft objects can sometimes be retrieved with a flexible scope, but anything large, firm or long-standing, and essentially all such cases in children, is safer through a rigid scope, because the airway stays controlled if the object is dropped during removal.
Airway collapse
In some patients the airway walls are soft and collapse on breathing out, trapping air and causing a barking cough and breathlessness that does not respond to inhalers. Assessment is done with the patient breathing, and treatment may involve a stent, sometimes placed temporarily first to test whether it helps before anything permanent is considered.
After a lung transplant
The join between the donor airway and the recipient airway can narrow, soften or partially break down in the months after transplantation. Left alone it can cost the patient the function of the transplanted lung. Managed with dilatation, cryotherapy, debridement and stenting, the lung is usually preserved. This is a specific area of Dr. Manjunath's practice, described in airway complications after lung transplant.
What can be done through a rigid bronchoscope?
| Technique | What it does | Typically used for |
|---|---|---|
| Mechanical coring | The bevelled tip of the rigid tube is used to core through obstructing tissue | Bulky tumour in a main airway, where an immediate result is needed |
| Balloon dilatation | A balloon is inflated inside the narrowing to stretch it open | Scar narrowing, post-transplant and post-intubation stenosis |
| Cryotherapy | Extreme cold destroys tissue or freezes material onto a probe for removal | Tumour, granulation tissue, blood clot, some foreign bodies |
| Electrocautery, argon plasma and laser | Heat cuts tissue and seals bleeding vessels | Bleeding tumour, granulation tissue, precise cutting of scar bands |
| Stent placement | A silicone or metal tube holds the airway open from inside | Obstruction that recurs, external compression, airway collapse |
| Foreign body retrieval | Large forceps and baskets pass through the open tube | Inhaled objects, especially in children |
In practice most cases combine several of these in one session, and a flexible scope is often passed through the rigid tube to reach further into the smaller airways.
Which airway stent is used, silicone or metal?
Silicone stents can be repositioned and removed later, which makes them the usual choice where the underlying problem is benign and may resolve, such as scar narrowing or a post-transplant stricture. They require a rigid scope to place, and they can migrate.
Self-expanding metallic stents are placed more easily and conform well to irregular airways, which suits malignant obstruction. Uncovered metal stents become embedded in the airway wall over weeks and are then extremely difficult to remove, so they are used with caution in benign disease where a patient may live for many years.
Every stent needs follow-up. Secretions collect, granulation tissue grows at the ends, and stents can move. Patients with a stent are given clear instructions on humidification and on the symptoms that should prompt an urgent call, and are seen for planned review bronchoscopy.
What happens on the day of a rigid bronchoscopy?
You will be seen beforehand for assessment and consent, with attention to your heart and lung reserve, any loose teeth or dental work, and your medications including blood thinners. Nothing to eat for six hours and nothing to drink for two. Recent imaging is reviewed, since the plan depends on exactly where the problem is and what lies beyond it.
In theatre, general anaesthesia is given and a mouth guard protects the teeth. The rigid scope is passed and ventilation continues through it. The obstruction is treated, a stent placed if needed, and the airways are cleared and checked before the scope comes out. Duration ranges from about 30 minutes for a straightforward dilatation to considerably longer for complex tumour work.
Recovery is in a monitored area. Some patients go home the same day; many stay overnight, particularly after stenting or tumour debulking. A sore throat, hoarse voice and some blood-streaked sputum are expected. Where a stent has been placed you will be taught how to humidify and given a plan for follow-up.
What are the risks of rigid bronchoscopy?
Practice standards for this work are set out in the British Thoracic Society guideline for advanced diagnostic and therapeutic flexible bronchoscopy. This is a more invasive procedure than flexible bronchoscopy, and it is offered when the alternative carries greater risk. Possible complications include bleeding during tumour removal, chipping or loosening of teeth as the tube passes, tearing of the airway wall, low oxygen during the procedure, airway swelling afterwards, and stent-related problems including migration, blockage by secretions and granulation tissue at the ends.
Individual risk depends far more on how unwell the patient is and how complex the airway problem is than on the technique itself. A patient with critical obstruction is at high risk from the obstruction whether or not anything is done, and that comparison is the one that matters in the consent conversation.
Where is rigid bronchoscopy done in Bangalore?
Rigid bronchoscopy needs three things in the same place: an operator trained and practised in it, an anaesthetist experienced in sharing an airway, and a centre that can manage a complication if one occurs. KIMS Electronic City has thoracic surgery on site and ECMO available, which matters in the small number of cases where an airway cannot be secured by conventional means.
Dr. Manjunath M Negigoudara holds a Fellowship in Interventional Pulmonology from Manipal Hospitals alongside MD in Pulmonary Medicine and DNB in Respiratory Medicine, and manages therapeutic airway work including the post-transplant airway. See the interventional pulmonology service.
If this is urgent
Central airway obstruction can deteriorate quickly. Seek urgent assessment for breathlessness that is worsening over days, noisy or whistling breathing audible without a stethoscope, inability to lie flat, coughing significant amounts of blood, or a known airway tumour or stent with new symptoms. Call +91 79937 41199 or attend the KIMS Electronic City emergency department. For referring physicians, an early call is always better than a late transfer.
For patients from Bangalore, across India, and abroad
Bengaluru and Electronic City
KIMS Hospital is on Hosur Road opposite the PES University EC Campus, about 15 minutes from Silk Board via the elevated expressway. Patients and referrals come from HSR Layout, Koramangala, Sarjapur Road, BTM Layout, Jayanagar, JP Nagar, Bannerghatta Road, Whitefield and Marathahalli, and from Bommasandra, Anekal, Chandapura and Attibele.
Karnataka and the rest of India
Because few centres offer therapeutic rigid bronchoscopy, patients are referred from across Karnataka including Mysuru, Mangaluru, Hubballi-Dharwad, Belagavi, Kalaburagi, Shivamogga, Tumakuru, Davangere and Ballari, and from Chennai, Coimbatore, Madurai, Salem, Hyderabad, Warangal, Vijayawada, Visakhapatnam, Tirupati, Kochi, Thiruvananthapuram, Kozhikode, Goa, Mumbai, Pune, Nagpur, Ahmedabad, Delhi NCR, Kolkata, Bhubaneswar, Guwahati, Lucknow, Patna, Ranchi and Raipur. For an obstructed airway, send the CT images on WhatsApp immediately rather than waiting for an appointment, because the urgency can be assessed from them. Kempegowda International Airport is about 45 km from the hospital.
International patients
Patients are referred from Bangladesh, Nepal, Sri Lanka, the Maldives and Bhutan, from Oman, the UAE, Saudi Arabia, Iraq, Yemen, Kuwait, Bahrain and Qatar, from Kenya, Tanzania, Ethiopia, Uganda, Rwanda, Sudan, Nigeria and Ghana, and from Myanmar, Indonesia and Malaysia. Imaging is reviewed over WhatsApp, a written opinion can support a medical visa application, and airway procedures are usually completed within a short admission with video follow-up afterwards.
Related reading
- Bronchoscopy, the flexible diagnostic procedure
- EBUS-TBNA, ultrasound-guided lymph node sampling
- Interventional pulmonology at KIMS Electronic City
- Airway complications after lung transplant
- ECMO, for respiratory failure that cannot be managed otherwise
- Second opinion on an airway obstruction plan
References
The clinical statements on this page are drawn from the peer-reviewed literature and international guidelines listed below. Each link opens the source on PubMed.
Frequently asked questions
What is the difference between rigid and flexible bronchoscopy?
Is rigid bronchoscopy done under general anaesthesia?
When is rigid bronchoscopy needed?
Can rigid bronchoscopy relieve breathlessness immediately?
What is an airway stent and how long does it stay in?
Is rigid bronchoscopy used after a lung transplant?
What are the risks of rigid bronchoscopy?
Where is rigid bronchoscopy available in Bangalore?
Next available
Book a consultation with Dr. Manjunath M Negigoudara
In person at KIMS Hospital, Electronic City, or by video